
 Gender Reassignment Surgery: Case Series of Chest Masculinization Surgery
Abstract
Introduction Chest masculinization surgery is one of the main procedures in the physical transition process of transgender men. The objective of the present study is to describe a series of cases of masculinizing mastoplasties and evaluate the results.
Materials and Methods The current is a primary, descriptive, interventional, longitudinal, and retrospective study. Two techniques were used: the periareolar and the double incision with autografting of the nipple-areolar complex. The photographic records for the comparison between the pre- and postoperative periods were analyzed by two plastic surgeons, who classified them as poor, fair, good, very good or excellent.
Results In total, 34 patients underwent surgery: most of them (32; 94.12%) underwent the double incision technique, and only 2 (5.88%) underwent the periareolar technique. A total of 2 patients (5.88%) underwent surgical reapproach due to hematomas. Regarding the evaluation by the judges, 14 (20.59%) results were classified as good, 29 (42.65%), as very good, and 25 (36.76%), as excellent. The observed agreement (Po) was of approximately 0.735, and the Kappa coefficient, of approximately 0.60.
Conclusion The experience of the main author (BPE) was reported, in addition to concepts about masculinizing mastectomy.
Keywords
plastic surgery; breast; nipple; transgender
Resumo
Introdução A cirurgia de masculinização do tórax é um dos principais procedimentos no processo de transição física de homens transgêneros. O objetivo deste estudo é descrever uma série de casos de mastoplastias masculinizadoras e avaliar os resultados.
Materiais e Métodos Este é um estudo primário, descritivo, intervencionista, longitudinal e retrospectivo. Duas técnicas foram utilizadas: a periareolar e a de dupla incisão com autoenxerto do complexo areolopapilar. Os registros fotográficos para a comparação entre o pré e o pós-operatório foram analisados por dois cirurgiões plásticos, que os classificaram como ruins, regulares, bons, muito bons ou excelentes.
Resultados Foram operados 34 pacientes: a maioria (32; 94,12%) foi submetida à técnica de dupla incisão, e somente 2 (5,88%), à técnica periareolar. Ao todo, 2 pacientes (5,88%) foram submetidos a uma nova abordagem cirúrgica por apresentarem hematomas. Quanto à avaliação pelos juízes, 14 (20,59%) resultados foram classificados como bons, 29 (42,65%), como muito bons, e 25 (36,76%), como excelentes. A concordância observada (PO) foi de aproximadamente 0,735, e o coeficiente Kappa, de cerca de 0,60.
Conclusão O estudo relata a experiência do autor principal (BPE), além de discutir conceitos sobre a cirurgia de mastoplastia masculinizadora.
Palavras-chave
cirurgia plástica; mama; mamilo; transgênero
Introduction
Gender incongruence or transgender identity refers to the misalignment between an individual's gender identity and their sex assigned at birth,1 and the term non-binary describes individuals whose gender identity exists outside or between the traditional male and female categories.2
Global estimates suggest that 0.5 to 1.5% of the population experiences gender incongruence.3,4 These figures are likely underestimated due to underreporting caused by moral, emotional, or religious concerns, fear, or lack of awareness regarding the condition.2,4
Gender affirmation is a multidisciplinary therapeutic process involving hormone therapy and/or surgery to align physical characteristics with gender identity.1 For female-to-male (FtM) transitions, the surgical options include chest masculinization (mastectomies or masculinizing mastoplasties), pelvic surgeries (hysterectomy and bilateral oophorectomy), and genital procedures (phalloplasties).1 Chest masculinization is often the first—and sometimes the sole—surgical intervention,5-7 with high patient satisfaction rates, improved quality of life, and reduced gender dysphoria reported in studies.8,9
Objective
The objective of the present study was to describe a case series of masculinizing mastoplasties, to emphasize critical aspects of the procedure, and to evaluate the surgical outcomes.
Materials and Methods
The current is a primary, descriptive, interventional, longitudinal, and retrospective case series of patients from the main author's (BPE) private clinic who underwent masculinizing mastoplasties between July 2017 and June 2023.
The present study was performed in line with the principles of the Declaration of Helsinki, and approval was granted by the Internal Review Board of Hospital Daher Lago Sul, Brazil (IRB/HDLS) under number 6.739.563. All patients signed the free and informed consent form to participate in the study, including an authorization for publication of the images in Figs. 1-5.

Photographs of a 24-year-old transgender man. (A–C) Preoperative appearance (patient on hormone therapy). (D–F) 3-month postoperative result following masculinizing mastoplasty/mastectomy (double-incision technique with nipple-areolar complex grafting). Image orientations: A and D: frontal view; B and E: right profile; and C and F: left profile.

Photographs of a 24-year-old transgender man. (A–C) Preoperative appearance (patient on hormone therapy). (D–F) 3-month postoperative result following masculinizing mastoplasty/mastectomy (double-incision technique with nipple-areolar complex grafting). Image orientations: A and D: frontal view; B and E: right profile; and C and F: left profile.
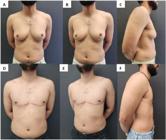
Photographs of a 34-year-old transgender man. (A–C) Preoperative appearance (patient on hormone therapy). (D–F) 3-month postoperative result following masculinizing mastoplasty/mastectomy (double-incision technique with free nipple-areolar complex grafting). Image orientations: A and D: frontal view; B and E: left oblique view; and C and F: right profile view.

Photographs of a 25-year-old transgender man. (A–C) Preoperative appearance (patient on hormone therapy). (D–F) 3-month postoperative result following masculinizing mastoplasty/mastectomy (periareolar technique). Image orientations: A and D: frontal view; B and E: right oblique view; and C and F: left profile view.

The inclusion criteria were defined as preoperative interdisciplinary and multidisciplinary team follow-up for a minimum one of 1 year, a minimum age of 18 years, and absence of a diagnosis of severe mental health disorder. The exclusion criteria were irregular postoperative follow-up and failure to sign the informed consent form.
All patients underwent preoperative breast imaging (ultrasound and/or mammography) to exclude pathologies contraindicating surgery. The surgical technique was selected by the primary surgeon and author of the current study (BPE) after a thorough physical evaluation and consultation, based on breast size, degree of ptosis (according to the Regnault classification), skin quality and elasticity (assessed via physical examination), and patient preference. All surgeries were performed by the same surgeon, who employed two techniques depending, on the case: the periareolar (for small, non-ptotic breasts) and the double incision with autologous grafting of the nipple-areolar complex (NAC) for medium/large or ptotic breasts.
The patients were followed postoperatively for a minimum of 5 months and a maximum of 12 months. The variables analyzed included age, self-identified gender, hormone therapy status (prior or concurrent), comorbidities, previous surgeries, surgical technique used, and procedural complications. Major complications were defined as those requiring reoperation, while minor complications were resolved in outpatient settings.
Comparative pre- and postoperative photographic records (3–6 months after surgery) were evaluated by 2 board-certified plastic surgeons, full members of the Brazilian Society of Plastic Surgery (Sociedade Brasileira de Cirurgia Plástica, SBCP, in Portuguese) with at least 5 years of experience in the field. The assessment parameters included alignment of results with a masculine chest contour, scar positioning relative to the inframammary fold (IMF) and the esthetic quality of the scars, as well as the shape and positioning of the NAC. The results were submitted to a global analysis of outcomes, and they were classified as poor, fair, good, very good or excellent.
Results
A total of 34 underwent masculinizing mastoplasty. Their mean age was 27.05 (range: 19–41 years). Most patients (28; 82.35%) identified as male, while 6 (17.65%) identified as non-binary. The most prevalent comorbidities were anxiety disorder (23.53%), overweight (23.53%) and depression (11.76%). Demographic details are presented in Table 1.
Demographic data of patients who underwent masculinizing mastoplasty/mastectomy between July 2017 and June 2023
At the time of surgery, 32 patients (94.12%) were on hormone therapy. Only 1 (2.94%) patient had previously undergone another gender-affirming procedure (hysterectomy).
Most patients (32; 94.12%) underwent the double-incision technique with free NAC grafting, while only 2 (5.88%) were treated via the periareolar approach. Notably, in 1 (2.94%) case, despite being a candidate for the periareolar technique, the patient elected to proceed with the double-incision method.
A total of 2 (5.88%) patients required surgical reintervention on posmiddleerative day 1 due to hematoma formation. In both instances, the suture line over the affected hemithorax was reopened, hemostasis was achieved, and the incision was reclosed. Both patients experienced an uneventful recovery following these interventions.
The overall incidence of minor complications was of 23.52% (8 cases), as detailed in Table 2. The most common issues were epidermolysis and small dehiscences of the grafted areas. These minor complications were managed successfully with serial dressings. The single case of an unesthetic (hypertrophic) scar demonstrated marked improvement thorughout the ensuing months with the application of silicone gel.
Surgical techniques and complications of masculinizing mastoplasties/mastectomies performed between July 2017 and June 2023
Regarding the judges' evaluations, showed in Table 3, 14 (20.59%) outcomes were rated as good, 29 (42.5%), as very good, and 25 (36.76%), as excellent. No poor or fair ratings were recorded. The observed agreement (PO) was of approximately 0.735, and the Cohen's Kappa coefficient was of approximately 0.60. Figs. 1-2 3 4 illustrate some of the results achieved.
Evaluation by judges of the postoperative results of masculinizing mastoplasties conducted between July 2017 and June 2023
Discussion
Population with Gender Incongruence and Healthcare Needs
Medical assistance for transgender patients should provide integral, specialized care across all stages—initial intake, outpatient follow-up, hormone therapy, clinical and surgical procedures, and posmiddleerative monitoring. This continuum of care is typically delivered by a multidisciplinary team—composed of psychiatrists, endocrinologists, gynecologists, urologists, and plastic surgeons, among others—to support the patient's needs and decision-making in its full complexity.1
Improvement in Dysphoria and the Importance of Surgical Procedures
Numerous studies2,5,10 report that transgender individuals frequently experience discrimination, stigma, and abuse. Alarmingly, 41% of transgender people report having attempted suicide—compared with 1.6% of the general population—and 56% have been diagnosed with depression at some point (approximately 4 times the rate for the general population), while 38% have been diagnosed with anxiety (50% higher than the general rate).4
In the present case series, 8 out of 34 patients (23.53%) had a history of anxiety or depressive disorder and the same number were classified as being overweight, which is often linked to anxiety and depression.
One study11 demonstrated that, 1 year after surgery, 96% of the patients reported feeling comfortable with their bodies in the workplace, and 43% felt comfortable exposing their bodies in public settings such as pools and beaches. These findings underscore the functional and psychological benefits of masculinizing chest surgery for this population.
Collectively, the data affirms that plastic surgery plays a pivotal role in gender affirmation, aiding individuals in aligning their phenotype with their identity and thereby contributing to a reduction in gender dysphoria and societal prejudice.
On Binders and Social Media
Many transgender men use compressive bandages—commonly known as binders—to flatten breast tissue and reduce the discomfort and social stigma associated with chest fullness.12,13 However, binders can be uncomfortable and may lead to pain, skin infections such as dermatitis, restricted upper-limb mobility, and breathing difficulties.12,13
Given the discomfort of prolonged binder use, many transgender men deliberately display their posmiddleerative scars as symbols of pride and community identity.10 In the current study, for example, one patient who qualified for the smaller-scar periareolar technique chose instead the double-incision approach—with its more prominent scarring—as a form of personal expression.
This celebration of surgical scars extends into social media platforms (Instagram, Facebook etc.), in which posts tagged with #middlesurgery, #ftm, and #transmen foster engagement and dialogue about masculinizing chest surgery. In this way, the linear scars of the chest become emblematic badges of individual triumph and collective solidarity.
Preoperative Preparation and Surgical Techniques
The periareolar technique yields small, well-concealed scars but has limited applicability, being suitable only for patients with small, non-ptotic breasts and good skin quality.14 For medium-to-large breasts or those with ptosis, the double-incision approach with free NAC grafting was chosen. Commonly called the smile technique due to the curved shape of the final inframammary scars resembling a smiling mouth, this method was the most frequently performed. Its advantages include excellent surgical exposure, relative technical ease, and low rates of revision surgery. The main drawbacks are long inframammary scars—which may extend laterally along the thoracic wall—and potential changes to the areolae, including contour irregularities and reduced sensation.5,7,15
Description of the Double-Incision Technique with Free NAC Grafting
The patient is marked in an orthostatic position (Fig. 5). A midline is drawn from the sternal notch to the umbilical scar, checking for any umbilical deviations to avoid affecting the remaining markings. The IMF is outlined bilaterally (this marking typically follows the inferior border of the pectoralis major muscle [PMM]). Next, this marking is transposed to the upper part of the breast, providing a preliminary outline of the dermoglandular tissue to be removed and the skin flap to be preserved.
Bilateral oblique markings are made from the umbilical scar to the anterior axillary pillar, which in most patients runs tangent to the lateral border of the PMM, similar to descriptions made by other authors.16,17 Subsequently, a dashed line is drawn from the medial third of the clavicle to the NAC.
Areas for liposuction, most commonly in the preaxillary or lateral thoracic regions, may be demarcated. It should be emphasized that the main skin flap areas should generally not undergo liposuction. Urinary catheterization is avoided, as the surgical time is limited to approximately 3 to 4 hours, and the procedure may cause discomfort for the patient due to genital exposure inconsistent with their phenotype. Antibiotic prophylaxis with cephalosporin is administered approximately 30 minutes before the surgical incision.
The procedure begins with infiltration of a 0.9% saline solution and adrenaline (1:500 thousand) into the incision areas and lipodystrophy regions (axillary and lateral thoracic areas). After waiting approximately 7 minutes, liposuction is performed in the marked areas using a 4.0 cannula.
Next, the areolar grafts are harvested. For large areolas, the option is to perform dual resection of the areolar segment: the areola and nipple are resected and grafted separately.
After harvesting, the incision begins at the upper breast marking, aiming at complete removal of the NAC, as in cases of small breasts with large NACs, this could result in upward displacement of the fold incision. During mastectomy, an approximate thickness of 1.0 to 1.5 cm should be maintained in the superior flap to preserve proper vascularization and innervation without damaging the subdermal plexus, minimizing the risk of flap ischemia. To standardize the flap, excess subcutaneous tissue is resected with Metzenbaum scissors to avoid irregularities.
The lower incision follows, which may be made directly at the IMF or slightly above it in cases of very low-set breasts. Rigorous hemostasis is performed, and the cranial and caudal skin flaps are approximated.
The scar is typically oriented horizontally in the central portion of the chest. In the lateral portion, a more curvilinear line is preferred, mimicking the angle of the lateral border of the PMM, like that proposed by other authors.18 Connecting the scars in the sternal region is avoided, although it may be necessary in cases of large breasts or significant ptosis.
Regarding NAC reconstruction, the symmetrical positioning of the new NAC, its dimensions, and characteristics are fundamental to construct an esthetically-pleasing masculine chest.18-20 Grafting is preferred over an inferior pedicle dermal flap, as the latter requires maintaining more breast tissue for viability, which may result in excess volume in the breast region and an unsatisfactory outcome.
The literature indicates that approximately 91% of male areolas have an oval shape, with an approximate size of 1.5 × 2.5 cm.6,21,22 However, the devices available on the market to mark areolas are essentially round, designed based on the shape and size of female NACs.
Given that the standard male NAC has a different configuration, using commercially-available areolotomes, which were designed according to female anatomy, produces areolas with configurations distinct from those typically observed in men. Additionally, when grafted, NACs tend to elongate vertically due to skin tension and stretching, further distorting their shape.6,23
In this context, other authors6 have advocated specific adaptations after conventional circular skin marking, essentially flattening the original marking (reducing the vertical diameter and increasing the lateral extension). It is believed that this approach works with skin tension forces and traction vectors, avoiding less realistic results caused by a vertically elliptical shape. Thus, a pair of elliptical areolotomes (measuring 1.7 × 2.3 cm and 1.8 × 2.6 cm) made of stainless steel was designed and developed, based on the proportions of male areolas and craniocaudal traction forces. Thus, after harvesting and grafting in an oval shape, the goal is to maintain this appearance horizontally; or, when significant scar contraction occurs, the NAC evolves into a rounded shape, which is also esthetically pleasing and well-accepted by patients.
Regarding NAC positioning, it is located approximately 2.0 cm medially to the lateral border of the PMM and approximately 2.0 cm superiorly to its inferior insertion (where the IMF incision is placed). Generally, the NAC lies tangential to the oblique thoracic line initially marked and approximately 11 to 12 cm from the midsternal line. For patients with large areolas, the option is to harvest the areolar and nipple segments separately, enabling individual grafting of each component of the complex. For this, the areolar tissue is thinned, and the nipple tissue is left slightly thicker while also reducing its size.
Suction drains are left in the breast pocket for approximately 5 to 7 days and removed when the output is lower than 50 mL in 24 hours. Sutures are made with polyglactin sutures in the subcutaneous layer (deep layer: 3.0; and superficial layer: 4.0) and with monofilament nylon in the skin (4.0) and graft (5.0). The NAC graft dressing consists of a first layer of cellulose mesh soaked in essential fatty acids, followed by gauze under negative pressure covered with a transparent plastic dressing. This dressing is removed after approximately 5 to 7 days, and daily dressings with fatty acid-soaked gauze are recommended.
For posmiddleerative care, the use of antithrombosis stockings for 15 days and a chest binder for 45 days is advised. Anticoagulants are not prescribed. The NAC graft sutures are removed around 10 to 12 days posmiddleeratively, and the remaining sutures are kept for 20 to 30 days. Return to activities is gradual: driving and resuming normal activities are allowed after 3 weeks, and physical activities, after 6 weeks.
Peer Evaluation of Results
In the peer evaluation of the outcomes, the results were classified as excellent (25; 36.76%), very good (29; 42.65%) and good (14; 20.59%). The PO was of approximately 0.735, and the Cohen Kappa coefficient, of approximately 0.60, indicating moderate to substantial inter-rater reliability.
Conclusion
The current study presents the principal author's (BPE) experience and discusses key concepts in chest masculinization surgery, to broaden the dissemination of this surgical approach among peers. The findings respond to the growing demand for gender-affirming procedures amid rising societal awareness of gender self-determination.
Data Availability
Data will be available upon request to the corresponding author.
References
-
1 Conselho Federal de Medicina (CFM) Resolução CFM n° 2.265/2019. Dispõe sobre o cuidado específico à pessoa com incongruência de gênero ou transgênero e revoga a Resolução CFM n° 1.955/2010 Revogada pela Resolução CFM n° 2.427/2025. Brasília: Diário Oficial da União; 2020. Available from: https://sistemas.cfm.org.br/normas/visualizar/resolucoes/BR/2019/2265
» https://sistemas.cfm.org.br/normas/visualizar/resolucoes/BR/2019/2265 -
2 Spizzirri G, Eufrásio R, Lima MCP, et al. Proportion of people identified as transgender and non-binary gender in Brazil. Sci Rep 2021;11(01):2240. Doi: 10.1038/s41598-021-81411-4
» https://doi.org/10.1038/s41598-021-81411-4 -
3 McEvenue G, Xu FZ, Cai R, McLean H. Female-to-male gender affirming top surgery: a single surgeon's 15-year retrospective review and treatment algorithm. Aesthet Surg J 2017;38(01): 49–57. Doi: 10.1093/asj/sjx116
» https://doi.org/10.1093/asj/sjx116 -
4 Winter S, DiamondM, Green J, et al. Transgender people: health at the margins of society. Lancet 2016;388(10042):390–400. Doi: 10.1016/S0140-6736(16)00683-8
» https://doi.org/10.1016/S0140-6736(16)00683-8 -
5 Berry MG, Curtis R, Davies D. Female-to-male transgender chest reconstruction: a large consecutive, single-surgeon experience. J Plast Reconstr Aesthet Surg 2012;65(06):711–719. Doi: 10.1016/j.bjps.2011.11.053
» https://doi.org/10.1016/j.bjps.2011.11.053 -
6 Agarwal CA, Wall VT, Mehta ST, Donato DP, Walzer NK. Creation of an aesthetic male nipple areolar complex in female-to-male transgender chest reconstruction. Aesthetic Plast Surg 2017;41 (06):1305–1310. Doi: 10.1007/s00266-017-0935-7
» https://doi.org/10.1007/s00266-017-0935-7 -
7 Marques B. Mastectomia masculinizadora para redesignação de gênero de transexuais masculinos. Rev Bras Cir Plást 2021;36(04): 390–396. Doi: 10.5935/2177-1235.2021RBCP0123
» https://doi.org/10.5935/2177-1235.2021RBCP0123 -
8 Van de Grift TC, Kreukels BP, Elfering L, et al. Body image in transmen: multidimensional measurement and the effects of mastectomy. J Sex Med 2016;13(11):1778–1786. Doi: 10.1016/j.jsxm.2016.09.003
» https://doi.org/10.1016/j.jsxm.2016.09.003 -
9 Van de Grift TC, Elfering L, Greijdanus M, et al. Subcutaneous mastectomy improves satisfaction with body and psychosocial function in trans men: findings of a cross-sectional study using the BODY-Q Chest Module. Plast Reconstr Surg 2018;142(05): 1125–1132. Doi: 10.1097/PRS.0000000000004827
» https://doi.org/10.1097/PRS.0000000000004827 - 10 Elias N, Rysin R, Kwartin S, Wolf Y. Breaking the binary: the approach to chest masculinizing gender-affirming surgery in transgender men. Isr Med Assoc J 2022;24(01):20–24
-
11 Alcon A, Kennedy A, Wang E, et al. Quantifying the psychosocial benefits of masculinizing mastectomy in transmale patients with patient-reported outcomes: the University of California, San Francisco, Gender Quality of Life Survey. Plast Reconstr Surg 2021;147(05):731e–740e. Doi: 10.1097/PRS.0000000000007883
» https://doi.org/10.1097/PRS.0000000000007883 -
12 Cohen WA, Shah NR, Iwanicki M, Therattil PJ, Keith JD. Female-to-male transgender chest contouring: a systematic review of out-comes and knowledge gaps. Ann Plast Surg 2019;83(05): 589–593. Doi: 10.1097/SAP.0000000000001896
» https://doi.org/10.1097/SAP.0000000000001896 -
13 Peitzmeier S, Gardner I, Weinand J, Corbet A, Acevedo K. Health impact of chest binding among transgender adults: a community-engaged, cross-sectional study. Cult Health Sex 2017;19(01): 64–75. Doi: 10.1080/13691058.2016.1191675
» https://doi.org/10.1080/13691058.2016.1191675 -
14 Wilson SC, Morrison SD, Anzai L, et al. Masculinizing top surgery: a systematic review of techniques and outcomes. Ann Plast Surg 2018;80(06):679–683. Doi: 10.1097/SAP.0000000000001354
» https://doi.org/10.1097/SAP.0000000000001354 -
15 Junn A, Khetpal S, Smetona J, et al. Hockey stick incision: a modified technique for chest wall masculinization. Ann Transl Med 2021;9(07):600. Doi: 10.21037/atm-20-7678
» https://doi.org/10.21037/atm-20-7678 -
16 Atiyeh BS, Dibo SA, El Chafic AH. Vertical and horizontal coordinates of the nipple-areola complex position in males. Ann Plast Surg 2009;63(05):499–502. Doi: 10.1097/SAP.0b013e3181953854
» https://doi.org/10.1097/SAP.0b013e3181953854 -
17 Tanini S, Calabrese S, Lo Russo G. The importance of nipple-areola complex position in chest masculinization surgery. Aesthetic Plast Surg 2021;45(02):829–830. Doi: 10.1007/s00266-020-01707-0
» https://doi.org/10.1007/s00266-020-01707-0 -
18 Ammari T, Sluiter EC, Gast K, Kuzon WM Jr. Female-to-male gender-affirming chest reconstruction surgery. Aesthet Surg J 2019;39(02):150–163. Doi: 10.1093/asj/sjy098
» https://doi.org/10.1093/asj/sjy098 -
19 Ayyala HS, Mukherjee TJ, Le TM, Cohen WA, Luthringer M, Keith JD. A three-step technique for optimal nipple position in transgender chest masculinization. Aesthet Surg J 2020;40(11): NP619–NP625. Doi: 10.1093/asj/sjaa150
» https://doi.org/10.1093/asj/sjaa150 -
20 Lo Russo G, Tanini S, Innocenti M. Masculine chest-wall contouring in FtM transgender: a personal approach. Aesthetic Plast Surg 2017;41(02):369–374. Doi: 10.1007/s00266-017-0796-0
» https://doi.org/10.1007/s00266-017-0796-0 -
21 Beer GM, Budi S, Seifert B, Morgenthaler, Infanger M, Meyer VE. Configuration and localization of the nipple-areola complex in men. Plast Reconstr Surg 2001;108(07):1947–1952, discussion 1953. Doi: 10.1097/00006534-200112000-00015
» https://doi.org/10.1097/00006534-200112000-00015 -
22 Tanini S, Lo Russo G. Shape, position and dimension of the nipple areola complex in the ideal male chest: a quick and simple operating room technique. Aesthetic Plast Surg 2018;42(04): 951–957. Doi: 10.1007/s00266-018-1131-0
» https://doi.org/10.1007/s00266-018-1131-0 -
23 Mundinger GSS. Double-sided nipple-areola complex marker for masculinizing chest surgery. Plast Reconstr Surg Glob Open 2021; 9(09):e3792. Doi: 10.1097/GOX.0000000000003792
» https://doi.org/10.1097/GOX.0000000000003792
Edited by
-
Editor-in-Chief:
Dov Charles Goldenberg.


